

Executive Overview
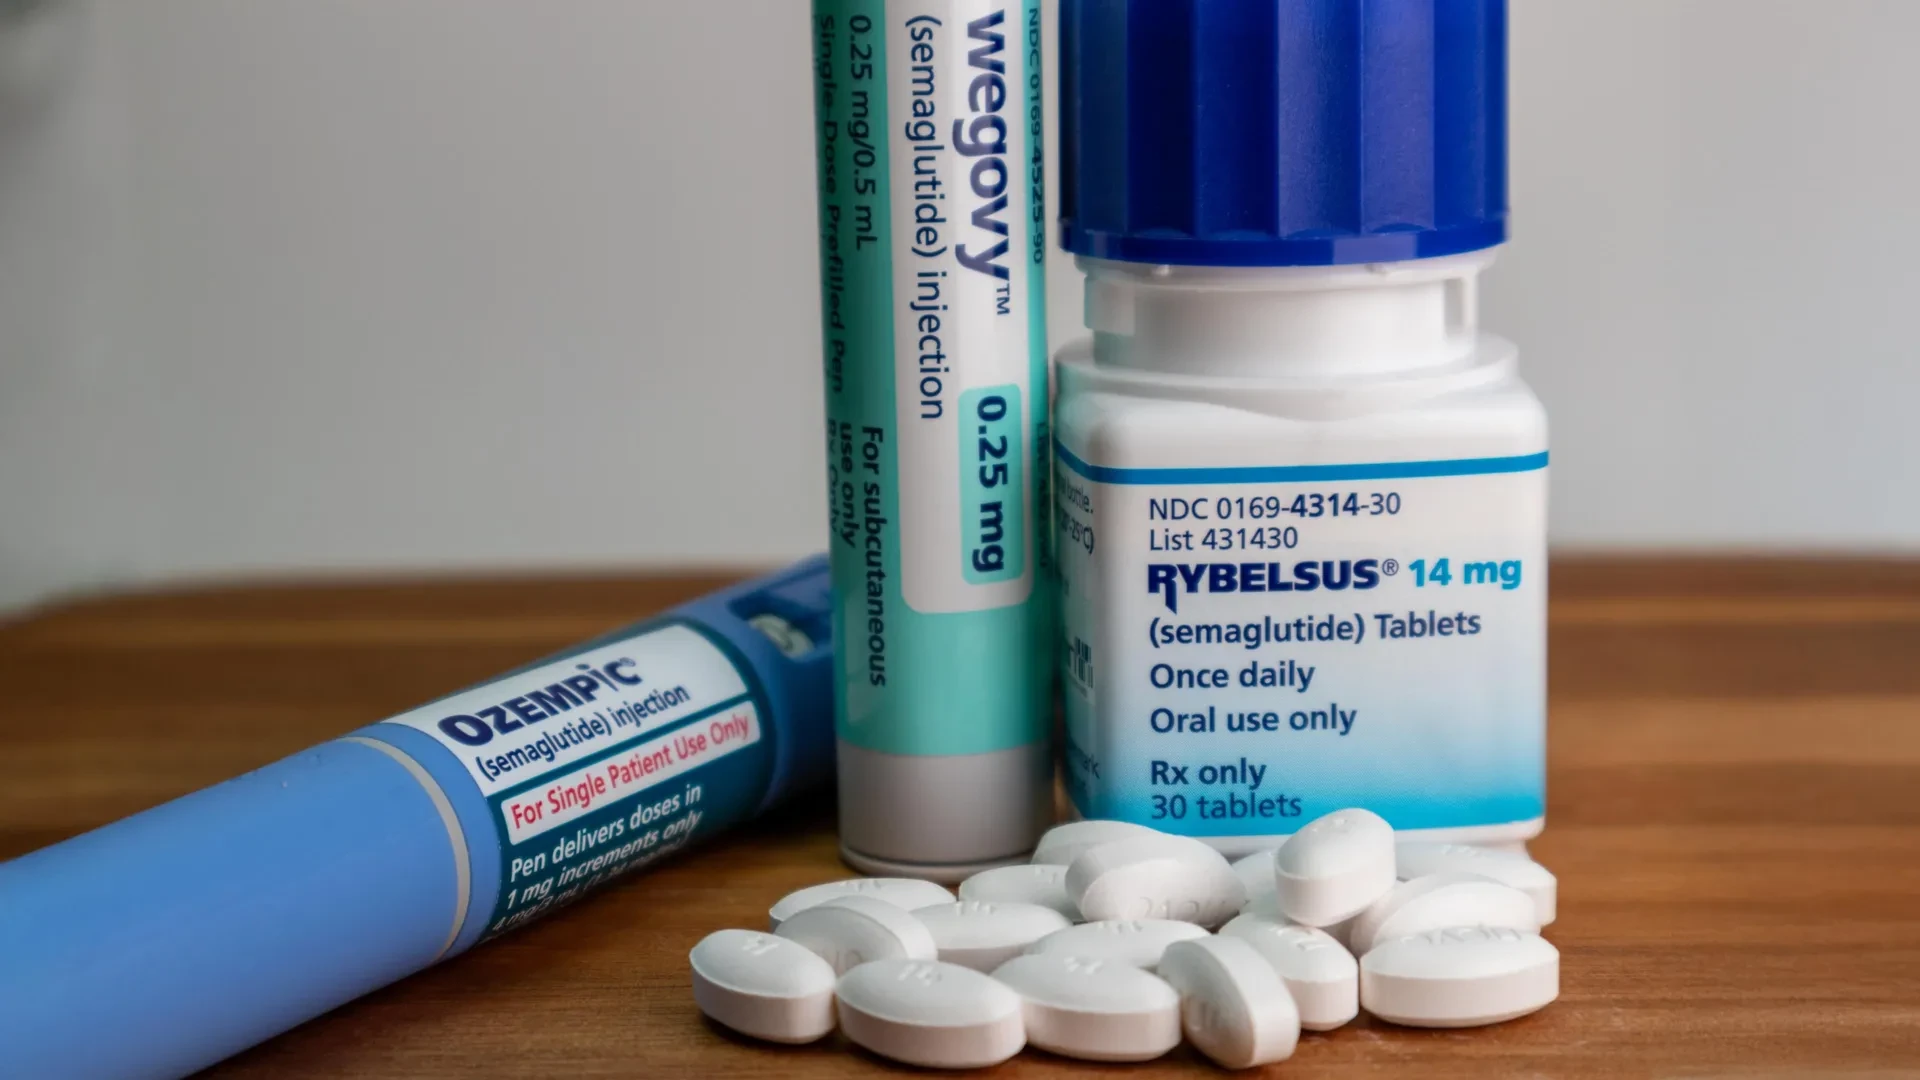
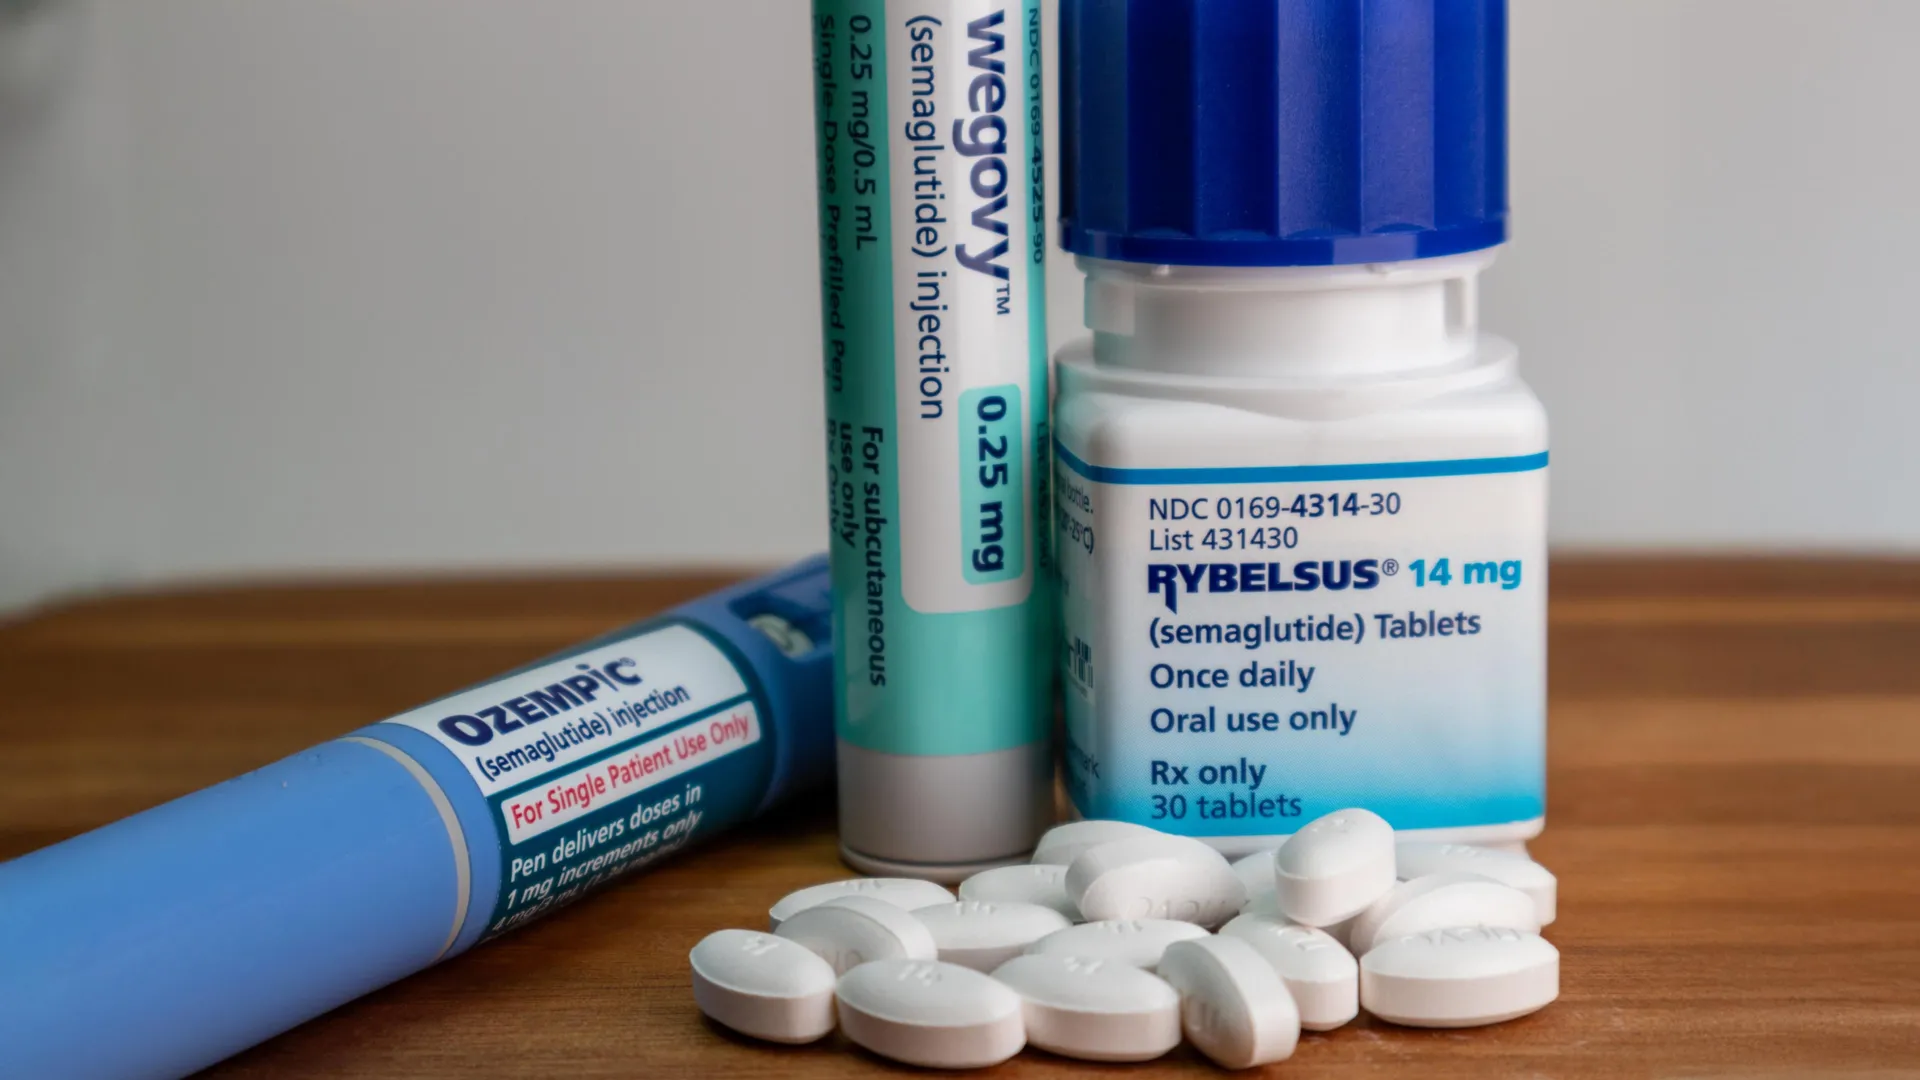
In the span of just a few years, medications containing semaglutide—a GLP-1 (glucagon-like peptide-1) receptor agonist initially developed to manage type 2 diabetes—have fundamentally transformed the landscape of modern medicine. Marketed under household names like Ozempic and Wegovy, these breakthrough therapeutics have evolved from specialized glycemic controllers into cornerstone pillars of global obesity management. Clinical trials and real-world applications have repeatedly demonstrated their remarkable efficacy, showing that weekly administrations combined with targeted lifestyle interventions can help patients shed an average of 15 percent of their total body weight over a 68-week period.
Yet, as millions of patients turn to these therapies, clinicians and researchers face a persistent clinical conundrum: semaglutide does not work the same way for everyone. While some individuals experience profound, life-altering weight loss and metabolic improvements, others see minimal results or encounter frustrating weight-loss plateaus.
To bridge this critical gap in patient care, a multidisciplinary research team at the University of Alberta is spearheading an investigation into the complex mechanics of human biology. Moving far beyond the simple scale-reading metric of weight loss, these researchers are exploring the intricate interplay of genetics, body composition, individual metabolism, and, crucially, energy utilization. By unlocking how the human body adapts thermodynamically to pharmaceutical-induced weight loss, this research aims to pave the way for a new era of personalized medicine—one where physicians can accurately predict patient responses, preemptively identify non-responders, and tailor obesity and diabetes treatments to the unique metabolic profile of every individual.
Detailed Chronology
To understand how the medical community arrived at the current frontier of semaglutide research, it is essential to trace the historical progression of obesity science, pharmacological evolution, and metabolic tracking.
- The Pre-GLP-1 Era and Traditional Weight Loss: For decades, obesity was overwhelmingly mischaracterized as a mere failure of willpower, treated primarily through blunt caloric restriction and intensive exercise regimens. While these lifestyle interventions remain vital, historical data consistently showed high rates of weight regain. The physiological pushback from the body—driven by ancient evolutionary survival mechanisms—frequently undermined long-term success.
- The Discovery and Rise of GLP-1 Receptor Agonists: The foundational science began to shift with the discovery of incretin hormones, specifically GLP-1. Researchers found that GLP-1 not only stimulates insulin secretion in a glucose-dependent manner but also acts directly on the central nervous system to suppress appetite and enhance the sensation of satiety (fullness). This paved the way for the development of long-acting peptide analogs like semaglutide.
- Clinical Validation and Broad Adoption: Landmark clinical trials—such as the Semaglutide Treatment Effect in People with Obesity (STEP) program—systematically documented unprecedented weight-loss figures alongside sweeping improvements in cardiovascular markers, glycemic control, blood pressure, and overall quality of life. Semaglutide transitioned rapidly from clinical journals into global public discourse.
- The Recognition of Variable Responses: As prescriptions scaled globally, clinicians noted a wide variance in patient outcomes. While the population average hovered near a 15 percent reduction in body weight, individual trajectories diverged wildly. Some patients excelled, while others experienced attenuated responses or plateaued early in their treatment cycle.
- The Current Investigational Frontier (Present Day): Recognizing that standard protocols require refinement, advanced research centers like the University of Alberta have launched targeted prospective studies. Utilizing state-of-the-art whole-room indirect calorimeters, contemporary researchers are actively tracking cohorts of patients starting semaglutide therapy. By mapping continuous energy expenditure against real-time body composition changes over six-month windows, science is moving from population-level averages to individual-level predictability.
Supporting Context & Metrics
Evaluating the true clinical impact of semaglutide requires looking far beyond the bathroom scale. Modern obesity medicine views weight loss not as an isolated cosmetic goal, but as a multi-system metabolic intervention.
Beyond the Scale: Comprehensive Health Markers
Extensive peer-reviewed literature confirms that the benefits of GLP-1 receptor agonists extend across numerous physiological domains. Clinical investigations demonstrate notable enhancements in:
- Glycemic Control: Significant reductions in glycated hemoglobin (HbA1c) levels for patients suffering from type 2 diabetes and insulin resistance.
- Cardiovascular and Lipid Profiles: Favorable shifts in systemic blood markers, including reductions in atherogenic cholesterol and systemic inflammatory markers.
- Functional Capacity: Documented improvements in muscular strength, mobility, and overall physical quality of life.
The Thermodynamics of Human Energy Metabolism
At the core of the University of Alberta’s current investigation is energy metabolism—the mathematical balance of total calories consumed versus total calories burned. Human energy expenditure is divided into three primary components:
- Basal Metabolic Rate (BMR): The energy required to sustain vital autonomic processes like breathing, cellular repair, and brain function at rest.
- Thermic Effect of Food (TEF): The energy expended in digesting, absorbing, and metabolizing nutrients.
- Activity Energy Expenditure (AEE): The calories burned through structured exercise and non-exercise activity thermogenesis (NEAT), such as fidgeting, walking, and daily occupational movements.
The Trap of Metabolic Adaptation
When an individual loses weight, the body’s absolute energy demand naturally decreases because there is less tissue to maintain. However, human biology frequently initiates an exaggerated response known as metabolic adaptation (or adaptive thermogenesis).
Metabolic adaptation occurs when the body enters an accelerated "energy-saving mode," burning significantly fewer calories than predicted by the new, lower body mass alone. Analogous to an automated smart-home lighting system that dims its bulbs to conserve electricity, the human body actively fights against perceived starvation by suppressing its metabolic rate. This biological defense mechanism is a primary catalyst for weight-loss plateaus and post-intervention weight regain, complicating the long-term efficacy of any weight-management strategy.
Body Composition and Resting Energy Use
Both fat tissue (adipose mass) and fat-free mass (muscle, bone, and visceral organs) consume energy, even during periods of complete rest. As individuals undergo rapid weight loss—whether via lifestyle modification or pharmacotherapy—they inevitably lose a combination of fat and fat-free mass.
Because fat-free mass is metabolically active and highly demanding of energy, its reduction directly lowers resting energy expenditure. A central question currently occupying clinical researchers is whether semaglutide influences these internal metabolic processes differently than traditional caloric restriction, and whether specific interventions can mitigate adaptive thermogenesis to preserve lean muscle mass.
Official Statements & Research Perspectives
The complexities of metabolic adaptation and the future direction of personalized obesity care have been highlighted by leading researchers and academic institutions dedicated to shifting the paradigm of metabolic medicine.
The multidisciplinary research team at the University of Alberta emphasizes that contemporary obesity care must evolve past generalized treatment models. In summarizing the objectives of their ongoing work, investigators note that identifying the precise physiological variables driving individual responses to semaglutide is essential for modern clinical practice.
"Understanding how semaglutide influences energy use and body composition, and how these changes interact, could be an important step toward explaining why individuals respond differently to weight-loss treatment," research communications from the University of Alberta note.
Furthermore, the academic team stresses the clinical necessity of moving toward predictive frameworks:
"This will allow us to contribute to more personalized approaches to obesity and Type 2 diabetes management in the future. Having a better understanding of how energy use changes with semaglutide-induced weight loss will also help us to better anticipate potential non-responders (people who do not lose weight) and offer alternative treatments sooner in their health journey."
By acknowledging that current scientific reviews of GLP-1 therapies and resting energy expenditure have yielded neutral or inconclusive results, the academic community underscores that metabolic adaptation during pharmaceutical treatment remains an open, highly dynamic field of study requiring rigorous, gold-standard empirical measurement.
Future Outlook
The trajectory of obesity pharmacotherapy points toward an increasingly sophisticated, individualized future. As research facilities continue to harness rare technologies—such as the whole-room indirect calorimeter at the University of Alberta, which operates much like an advanced residential suite capable of precisely parsing out resting, post-prandial, and exercise-induced energy expenditure—the "black box" of human metabolism is gradually being illuminated.
1. Predictive Diagnostics and Stratified Medicine
In the coming years, the integration of multi-omic data—spanning genetics, baseline metabolism, gut microbiota composition, concurrent morbidities, age, and biological sex—will likely enable clinicians to run predictive profiling before prescribing a GLP-1 receptor agonist. Instead of a trial-and-error approach, physicians will be able to determine whether a patient is primed for an optimal response to semaglutide or whether an alternative or combination therapy is indicated from day one.
2. Mitigating Metabolic Adaptation
As clinical trials follow patient cohorts over extended periods, researchers aim to design targeted physical, nutritional, and pharmacological protocols that counteract adaptive thermogenesis. By identifying ways to protect fat-free mass and prevent the sharp downturns in resting energy expenditure, future care models will help patients sustain their weight-loss achievements indefinitely, minimizing the frustrating cycles of weight regain and plateaus.
3. Redefining Standard Lifestyle Integration
Current clinical consensus dictates that medication alone is insufficient. Sustainable success with semaglutide requires enduring lifestyle modifications, including structured resistance training to preserve muscle mass, optimized nutritional intake to support metabolic health, and behavioral support systems. As the science of energy utilization matures, these lifestyle prescriptions will become increasingly granular, customized precisely to an individual’s measured metabolic output.
Ultimately, the ongoing investigation into semaglutide and energy metabolism represents a profound shift in how modern medicine views metabolic disease. By decoding the body’s evolutionary survival mechanisms, medical science is moving closer to a comprehensive, compassionate, and highly personalized framework that promises to optimize health outcomes for patients across all demographics.
